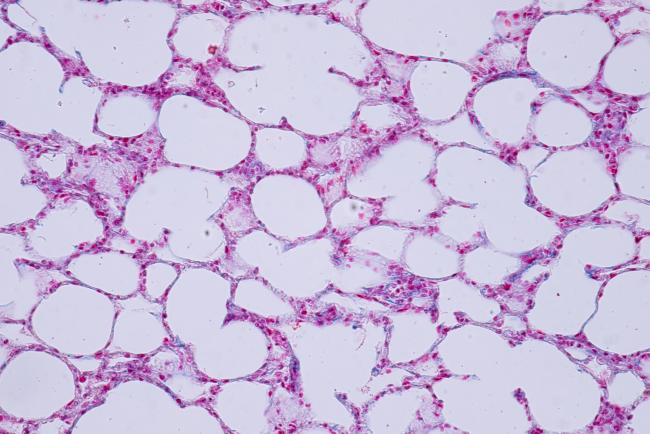
Human lung organoids with a built-in immune system could transform respiratory disease research
In NIH-funded study, the models orchestrated adaptive immune responses to viral infection.
Key points
- Focus: In NIH-funded study, the models orchestrated adaptive immune responses to viral infection
- Detail: separate announcement from evidence
- Editorial reading: institutional release, useful as a primary source but not independent validation.
In NIH-funded study, the models orchestrated adaptive immune responses to viral infection. The institutional report frames the development in practical terms and ties it to the broader mission or observing effort.
That matters because biology becomes more informative when an observed effect begins to look like a mechanism rather than an isolated pattern. The gap between identifying a correlation in biological data and understanding the causal chain that produces it is routinely underestimated, and the history of biomedical research is populated with associations that collapsed when the mechanism was sought and not found. A result that comes with a proposed mechanism, even a partial one, is more useful than a purely descriptive finding because it generates testable predictions that can narrow the hypothesis space. A new organoid model built with human lung fragments may help us answer key questions about one of the body’s first lines of defense against respiratory pathogens. In a National Institutes of Health (NIH)-supported study, researchers at the Stanford University School of Medicine elicited virus-specific immune responses from these organoids.
Powers III, M. D, acting director of NIH’s National Institute of Allergy and Infectious Diseases (NIAID). This platform may provide a replacement for animal models for some types of evaluations and may provide insights that tests in animal models could not capture.
The authors sustained organoids within this 3D air-liquid interface for up to several months, during which they found many critical immune cell populations thriving. Infecting organoids with SARS-CoV-2, the researchers saw that the lung models countered with not only generic immune reactions such as inflammation, but also adaptive responses.
Again, the organoid’s immune cells learned how to better detect and dispatch SARS-CoV-2, which diminished future infections. NIH supported this research through NIAID grants T32AI007502.
The broader interest lies in whether the reported effect points toward a real mechanism and not merely a reproducible but unexplained association. Biology has learned from decades of biomarker failures that correlation, even robust correlation, is not a substitute for mechanistic understanding. A pathway that can be traced from molecular interaction to cellular response to organismal phenotype provides a far stronger foundation for intervention than a statistical association discovered in a large dataset, however well the statistics are done.
National Institute of General Medical Sciences (NIGMS) grant T32GM007365. National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) grant R01DK130414, and National Cancer Institute (NCI) grant OT2CA278713.
Because the account originates with NIH News Releases, it functions best as a primary institutional report that is close to the data and operations, not as independent scientific validation. Institutional communications are produced by organizations with legitimate interests in presenting their work in a favorable light, which does not make them unreliable but does make them partial. Details that complicate the narrative, including instrument limitations, unexpected failures and results below projections, tend to be minimized relative to progress messages. Technical documentation and peer-reviewed publications, where they exist, provide the complementary layer that institutional releases cannot substitute.
The next step is to test whether the effect repeats across different methods, cell types, model organisms and experimental conditions. Reproducibility is the first test, but mechanistic dissection is the second, and a result that passes both has a substantially better chance of translating into something clinically or biotechnologically useful. The path from a laboratory finding to an applied outcome typically takes a decade or more, and most findings do not complete it; the current result sits at the beginning of that process.
Original source: NIH News Releases